Why Healthcare Documentation Drives Patient Safety and Quality
Healthcare documentation keeps care teams aligned and patients safe. Clear notes cut errors, support continuity across providers, and hold up legally.
Key Points
- In 2020, Bell and colleagues reported in JAMA Network Open that diagnosis errors led the very serious mistakes patients found in their own visit notes, at 27.5% .
- A 2011 Bern University Hospital study found a medication documentation error in 43% of patient charts , and 53% of the errors occurred at transcription onto the medication list.
- In Sermo's physician polling, 46% said leaving out the details that justify a clinical decision does the most to weaken a malpractice defense.

Quick Answer
Healthcare documentation drives patient safety because every clinical decision depends on the record. Accurate, timely notes carry allergies, medications, test results and reasoning across handoffs, so the next clinician acts on facts, not memory.
Gaps lead to medication errors and missed follow-ups. Volume is not the fix. In 2019, ONC's John Fleming, MD, argued that less burden lets physicians "provide more dedicated care," which points practices toward accurate charts rather than longer ones.
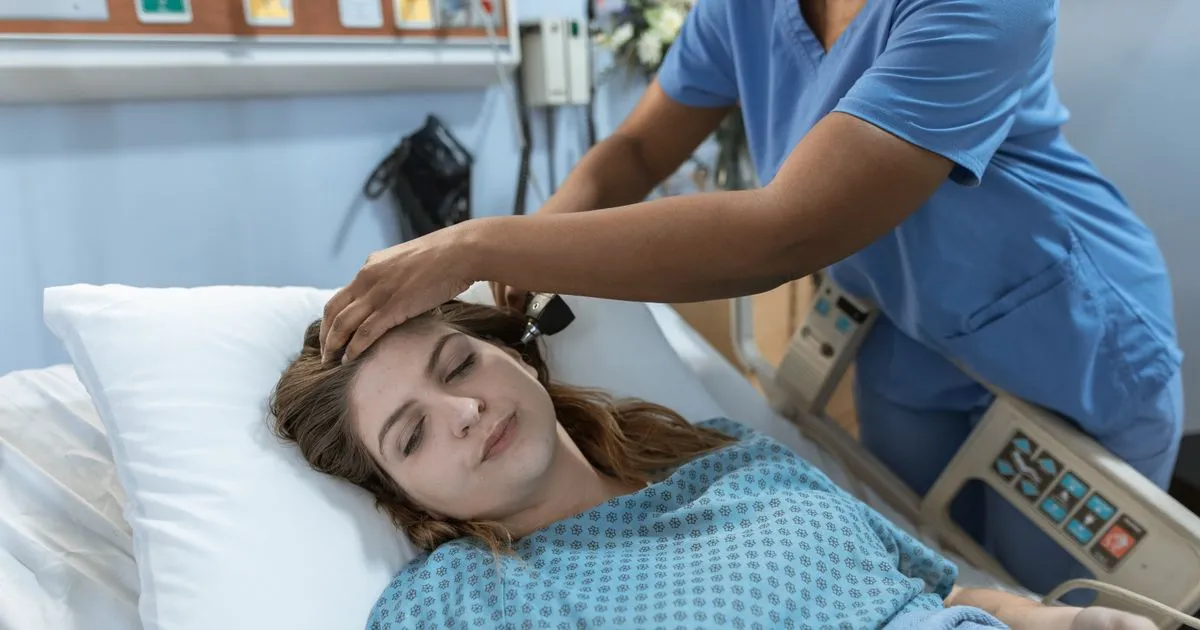
Every finding from a bedside ear exam, like this one, protects the patient only once it is recorded in her chart.
Clinical documentation is more than paperwork. It is the process of recording, managing and maintaining a patient's history, diagnosis, treatment and outcomes, and it is the one thing that travels with the patient from clinician to clinician.
Clinicians have said for years that it weighs on them. In 2019, when the Office of the National Coordinator for Health IT (ONC) held listening sessions with practicing clinicians, the top burden they named was "clinical documentation of care delivery," ranked ahead of prior authorizations, as ONC chief medical officer Tom Mason told Medical Economics. ONC's Andrew Gettinger, MD, described what doctors asked for. They don't want to go back to paper: "they just want the systems to work better."
Here is the trap. When documentation feels heavy, the instinct is to add more fields, more templates, more checklists. Yet over-documentation can lead to burnout and reduced focus on patient care. Auto-populated normal values can also hide abnormal findings when nobody actively overwrites them. So ask one question of every note: could a covering clinician act on it safely without calling anyone?
The pressure is rising, too. With the inpatient-only list going away completely by 2028, inpatient medical necessity documentation is set to matter more than ever.
In this article I walk through where documentation gaps turn into harm, why they persist inside modern EHRs, and what quality assurance should actually check. Why should a practice owner care? Because the patient whose allergy was spoken aloud but never written down is not a hypothetical. That patient could walk up to any front desk this week.
Healthcare documentation is the written record of what a patient reported, what a clinician found, what was decided and why. It matters for one plain reason: the next person who treats that patient acts on the record, not on anyone's memory.
Picture a patient who mentions a drug allergy out loud at check-in. Nobody charts it. Hours later, a covering physician opens the chart, sees no allergy listed, and writes a prescription. Who failed here? Not the physician. The record did.
Even a recorded allergy can fail the patient. When allergy information is buried in a free-text note instead of the dedicated allergy field, the EHR's automated safety checks never trigger a warning, and a single slip of the mouse can produce a 10-fold dosing error. The problem is not new, either. In 2011, a hospital study found documentation errors in 65 of 1,934 prescribed agents (3.5%), and every one of those was a dose someone might have given.
It's worth noting that the stakes reach past the bedside. A 2024 review commissioned by the Agency for Healthcare Research and Quality warned that documentation burden may affect patient outcomes, not only clinician burnout.
So the question I keep coming back to is not how much a chart holds. It is whether the one detail that matters, like that spoken allergy, made it into writing in the right field before the next clinician reached for the prescription pad.
How does a missing chart detail turn into patient harm?
A missing or wrong chart detail becomes harm the moment the next clinician trusts it and acts on it. Diagnosis, history, medication and allergy errors lead the serious list.
Before you rely on any note at a handoff, check five things:
- Are allergies recorded at all, and recorded clearly?
- Does every medication show dose, unit, route and frequency?
- Is the note signed, dated and time-stamped?
- Does the patient identity on the note match the person in front of you?
- Was any text copied forward from an older visit without review?
Each of those checks maps to a documented failure. In 2020, Bell and colleagues reported in JAMA Network Open that among the very serious mistakes patients found in their own visit notes, diagnosis errors led at 27.5%, followed by inaccurate medical history at 23.9% and medications or allergies at 14.0%. Another 23 very serious errors were notes reportedly written about the wrong patient.
Think about what that means for the next provider. Picture a patient whose allergy was mentioned out loud at check-in but never charted. The covering physician opens the record, sees no allergy, and prescribes. Nobody made a bad clinical decision. The record made it for them.
The common assumption is that medication errors start with a bad prescription. The data say otherwise. A 2011 study at Bern University Hospital's orthopedic unit found at least one medication documentation error in 43% of patient charts, and 53% of the errors occurred at transcription, when an order was copied from the prescribing sheet onto the patient's medication list. The order was written once. The mistake happened in the copy.
Electronic records have not removed that risk; they have moved it. Copied or imported text can carry outdated findings into today's note, and incomplete reasoning or delayed entries feed diagnostic error and communication failure. A unit slip such as mg vs. mcg, a missing laterality, or an unsigned note all look minor on screen. At the bedside they are not.
An analysis of 5 sources shows the same pattern: harm clusters where information is carried from one hand to the next. Transcription, copy-forward and handoff notes are the weak joints. Accuracy at those points = KEY.
That is also why I don't treat billing accuracy and clinical accuracy as separate problems at HelpSquad, which Clutch named a 2026 Top Medical Billing Company. The same missing detail that misleads a clinician will usually mislead a claim too. If you are sorting out which administrative tasks can safely move off your clinicians' plates, our guide on what to outsource in your medical practice walks through where that line sits, and why the chart itself still has to be right before anyone downstream touches it.
Which chart errors do the most damage, and where do they start?
Ask physicians which documentation mistake they see most often and they name one habit. Ask which mistakes hurt patients most and their answers point somewhere else.
Sermo, an online community of physicians, polled its members on both questions. The most common error was copying, pasting or cloning notes without review, at 33%. On patient harm, the top answer was failing to clearly document critical test results or follow-up instructions (31%), then inaccurate medication reconciliation or dosage entries (25%), then not documenting communication between professionals (21%). Someone else relies on each of those three details later: the clinician who reads the result, gives the next dose or takes over the case.
Patients see the same weak spots from the other side of the record. Dr. Sigall Bell of Beth Israel Deaconess Medical Center led a survey of patients who read their visit notes online, published in JAMA Network Open in 2020. Among those who read a note, 21.1% reported a mistake, and 42.3% of them called it serious. Of the errors patients called very serious, 58.9% involved at least one perceived error tied to the diagnostic process, such as history, examination, tests, referrals and communication. Older and sicker patients were twice as likely to report a serious error.
Malpractice claims show a gap that remains even when every action is charted. Sermo cites a 2024 report from Candello, a database of U.S. medical professional liability claims: nearly 20% of malpractice cases involve documentation failures, and missing rationales went with higher odds of a payout. In Sermo's polling, 46% of physicians said that leaving out the details that justify a clinical decision does the most to weaken a defense.
"The most frequent error I see is the lack of clear clinical reasoning: actions are recorded, but not the rationale behind them."
Anonymous physician member, Sermo, 2026
Claims data measure legal exposure. They cannot show how often a missing rationale harms a patient. WTW, a risk advisory and insurance firm with its own interest in liability, connects the two directly: incomplete reasoning, delayed entries and misuse of EHR tools "contribute to diagnostic error, communication failure, and adverse outcomes." Our reading is that a clinician who inherits an action without its reason can see what was done but not whether it should continue.
So where do these errors enter the chart? Before electronic records were common, researchers at Bern University Hospital reviewed every chart from one 20-bed orthopedic unit for January 2005. At least one medication documentation error turned up in 43% of charts. The most error-prone step was copying a prescription onto the patient's medication list.
Electronic records removed the handwriting, which the Bern team rated bad or unreadable on 56% of prescriptions, but the step where information gets moved remains, now often as copying forward. Physicians in the Sermo poll blamed over-reliance on templates (37%) more than any other EHR problem. The open-notes researchers suggested that overburdened practitioners may "import inaccurate medication lists" or carry older parts of the record forward by copying and pasting.
Quality assurance can fail the same way. The VA Office of Inspector General inspected the Tuscaloosa VA Medical Center in Alabama after an acting patient safety manager found more than 160 safety event reports still open. Amanda Newton of the inspector general's office described a program that had prioritized "resolving the issues themselves over ensuring completion of the documentation." She also said supervisors "just sort of trusted the word of the patient safety manager and didn't verify."
100%
Of the final safety event reviews in two years of Tuscaloosa data, every one lacked the documentation required to count as a complete investigation, according to Trina Rollins of the VA Office of Inspector General. Without that documentation, she said, "there's no way there for the facility to know if the system vulnerability was ever addressed."
Each of these sources looks at the record from a different angle, yet the serious errors keep showing up where information moves: a prescription copied onto a list, a template carried into today's note, a test result passed to the next clinician, a decision charted without its reason, a safety fix never written down. For those of us in quality assurance, putting every clinical detail in writing is the starting point, and the errors get caught by checking those details each time they change hands.
- Before signing a note built from a template or copied forward, check the medication list and allergies against their original source.
- Ask who owns each critical test result and follow-up instruction, and where in the chart that handoff is written down.
- In chart audits, check whether each assessment and plan records the reasoning behind a decision as well as the action taken.
- Invite patients to read their notes and report errors, starting with older and sicker patients, who reported serious errors twice as often.
- Treat a safety review as closed only when the investigation and the fix are written down and someone other than the reviewer has verified them.
How we checked this
We used a peer-reviewed patient survey, a single-unit chart review, physician polls, a risk advisory and two VA Office of Inspector General podcast interviews. None of the figures come from HelpSquad. The open-notes errors are what patients perceived, and no one independently verified them. Sermo's polls record physicians' opinions, not measured error rates. We saw the Candello figures only as Sermo summarized them. The Bern study covers handwritten charts on one unit in 2005, and the VA findings cover one facility. WTW sells risk and insurance services. We provide HIPAA-trained virtual assistants who take administrative work off healthcare practices, so we have a stake in arguing that clinicians' charting time matters. Still unknown: how often each type of error actually leads to harm. None of these sources measured that directly.
- Sigall K. Bell and colleagues, study of patient-reported errors in visit notes, JAMA Network Open, June 2020.
- Sermo, physician polls on documentation errors, including Candello claims figures, January 2026.
- WTW, documentation as a patient safety tool, July 2026.
- Maximilian J. Hartel and colleagues, Bern study of medication documentation errors, August 2011.
- Trina Rollins, VA OIG, Veteran Oversight Now podcast transcript, June 2023.
- Amanda Newton, VA OIG, Inside Oversight podcast transcript, July 2023.

Why do documentation gaps persist even with electronic health records?
Gaps persist because the workload, not the clinician, is the problem. Charting gets pushed to the end of the day, duplicated across screens, and squeezed between patients.
So if everyone knows a missing detail can hurt a patient, why does it keep happening? Because documentation burden is real, it is large, and nobody has agreed on how to measure it.
A 2024 systematic review commissioned by the Agency for Healthcare Research and Quality and led by the Mayo Clinic Evidence-Based Practice Center found 135 articles on measuring documentation burden, sorted into 11 categories ranging from total EHR time and inbox management to after-hours work and usability. Its verdict on those measures was blunt: evidence of their validity was "limited and incomplete." The same review ties the modern burden era to the 2009 HITECH Act and names "work outside of work" as a strong driver of burnout.
Read that again. Practices are asked to fix a problem the field still cannot measure well.
Clinicians describe the day-to-day version in plainer words. In a 2025 discussion among health informatics professionals, one commenter described having to write down everything from "8-10 hours of back to back to back patient facing visits" after the fact. Others pointed to flowsheets that don't flow, which means the same finding gets entered twice, and to software rollouts that skip proper training on the assumption that experience with an older system carries over. A former bedside nurse who moved into IT said they were the only clinical person on an EHR design team.
Nurses describe the same squeeze from the floor. One nurse with a year of experience estimated needing at least 2 hours per shift at the computer just to comb through charts and orders, while another reported carrying 8-12 patients with too few assistants to chart properly. When an EHR outage forced one unit back to paper, the nurse who started the thread said they were "A LOT faster" at vitals and medications.
Here is my read of what this adds up to. The documentation gap is mostly a structure problem:
- Timing: notes written hours later rely on memory, and memory blurs.
- Duplication: entering the same data twice invites the two entries to disagree.
- Standards: without a shared template, every clinician records the same visit differently.
- Capacity: when the patient load rises, the chart is the first thing cut short.
None of these is fixed by telling clinicians to try harder. Effort is not the scarce resource; time is.
That shifts the question from discipline to design. Which tasks around the chart actually need a licensed clinician, and which are scheduling, intake, insurance follow-up and data gathering that could be handled by trained medical virtual assistants so the clinician's minutes go to the clinical note itself? Answering that honestly is where real quality assurance begins.
What does real documentation quality assurance look like?
Quality assurance means reviewing a sample of real charts against a short list of what must be present, with a named owner for every gap found. At HelpSquad, the support staff who work around that record are HIPAA-certified through HIPAATraining.com.
That first clause is the whole principle. If it is not written down, the next person cannot act on it, audit it, bill it or defend it. Start with the allergy field: in each chart you sample, is the allergy coded where the EHR can check it, or buried in a free-text note?
What should be written down? Clinical documentation guidance published in 2025 lists the standard components of a complete record: patient identification, medical history, physical exam results, clinical notes, diagnostic test results, treatment plans, medication records, progress notes and discharge summaries. The same guidance notes that the Joint Commission and the Centers for Medicare & Medicaid Services require strict adherence to documentation standards, with audits, penalties and loss of accreditation as the cost of falling short.
Completeness alone is not quality, though. Physicians polled by Sermo said the documentation error that most weakens a malpractice defense is omitting the details that justify clinical decision-making, at 46%. And Sermo's review of a 2024 Candello claims report found that nearly 20% of malpractice cases involve documentation failures, with inconsistent entries or missing clinical rationales linked to more than doubled odds of a case closing with an indemnity payment.
So when you sample a note, ask whether a colleague could tell from it why the plan changed.
Here is how I'd turn that into checks a practice can run on a sample of charts every week:
| What to check | What good looks like | Why it matters |
|---|---|---|
| Core components | Identity, history, exam, results, plan and medications all present | Missing pieces force the next provider to guess |
| Clinical reasoning | The assessment explains why a decision was made | Rationale gaps drive both diagnostic error and liability |
| Copied text | Carried-forward findings reviewed and updated for today | Copy-paste or cloning without review was the most common error physicians reported, at 33% |
| Results and follow-up | Critical results and next steps clearly recorded | Physicians ranked failure to document these as the most harmful error, at 31% |
| Timing and sign-off | Entries made close to the encounter, signed and dated | Late notes rely on memory and lose detail |
One vendor in the documentation software space puts the stakes plainly, warning that an incorrect allergy entry on a chart could be fatal. Whatever you think of the pitch, the point stands.
The practical bind is obvious. Every check above takes clinician time, and the previous section showed how little of it is left. That is why I see QA as two jobs, not one: clinicians own the clinical content, and trained support staff own everything around it, from intake details and insurance data to chasing missing signatures before a claim goes out.
Where does healthcare documentation go from here?
The record will be judged on whether it carries reasoning, medications and patient identity across every handoff, not on its length. The next step is a small one: pull a handful of recent charts this week and check each for a coded allergy, a stated reason and a recorded follow-up.
WTW, the global risk advisory firm, named the core problem in 2026: a common documentation gap is recording what occurred without documenting why. Its six principles of high-quality documentation include one phrase I'd pin above every workstation: complete but not excessive.
A quick aside on AI scribes. Early evidence suggests ambient tools may reduce documentation burden, yet WTW notes that studies show inaccuracies occur and require clinician review. I'd accept that trade, but only if a human reads every line before signing.
Back to the patient whose allergy was spoken but never charted. They don't need a longer note. They need one accurate line in the right field. Clinicians own that line. The intake forms, insurance checks and callbacks around it can sit with trained support staff, which frees the minutes to write it before the next patient mentions, almost in passing, a drug that once made them sick.
Summarize This Article With AI
Open this article in your preferred AI engine for an instant summary.
Frequently Asked Questions
What else do people ask about healthcare documentation and patient safety?
Most questions come back to three things: which errors cause harm, whether the EHR helped, and how a practice frees clinicians to chart accurately without adding hours.
What are the most common documentation errors in healthcare?
Incomplete records top most lists: missing allergies, medication lists, dosages, laterality and time stamps. Wrong-patient entries, copy-and-paste cloning, unapproved abbreviations and unsigned or undated notes follow close behind. Each one hides what was actually ordered or verified.
What is note bloat?
Note bloat is manufactured documentation that is long on data but short on insight. It is often driven by a wish to avoid malpractice risk. The irony? It buries the one finding the next clinician needs.
Has the EHR made documentation better or worse?
Both, depending on who you ask. In a 2026 physician poll, 21% said quality had significantly improved thanks to legibility, 28% said slightly improved, and a combined 25% said it had worsened. Paper was no safer, though: in 2011, a Swiss hospital study rated 52% of handwritten prescriptions bad and 4% unreadable.
How is documentation burden measured?
Mostly through EHR usage logs. The Mayo Clinic team behind a 2024 federal review found that direct tracking, such as time and motion analysis, was "fairly uncommon." So the numbers a practice sees usually describe screen activity, not how well the record carries clinical reasoning.
What does HelpSquad charge for healthcare support staff?
HelpSquad charges $8 to $13 per hour for full-time staffing, as a fully managed service with HIPAA compliance, bilingual agents and dedicated account management. To talk through which front office tasks to outsource first, book an intro call at helpsquad.com/contact or call 877-775-3667.
Written by
Maria Rush
Marketing Team Lead, HelpSquad
Maria De Jesus-Rush is Marketing Team Lead at HelpSquad, a healthcare business process outsourcing company, with a background in content development, digital marketing, and project management.
Connect on LinkedIn
Healthcare Revenue Cycle Challenges and Fixes
Most healthcare revenue cycle failures are preventable front-end breakdowns. See what each one costs a practice and the fixes that recover revenue fastest.

Top Revenue Cycle Management Best Practices for 2026 Success
Healthcare RCM practices for 2026, covering AI claims tools that cut denials 30%, eligibility checks at service, and automated patient billing plans.
Understanding the Cost of AI in Healthcare
The cost of AI in healthcare goes past licenses, covering data cleanup, model validation, EHR integration, compliance review, and ongoing drift monitoring.
Let's talk about what your practice actually needs.
A 30-minute call. No sales pressure. We'll tell you honestly whether we're a fit.